Summary
IPG11406 is a first-in-class, orally administered small-molecule antagonist of EBI2 (GPR183) and the only EBI2-targeting agent in clinical development worldwide. Unlike current standard-of-care therapies, which primarily suppress inflammation or deplete immune cells systemically, IPG11406 is designed to act upstream, blocking the activation and tissue recruitment of pathological immune cells, thereby allowing inflammation to resolve without depleting immune cells. With a novel mechanism of action and encouraging clinical activity in lupus nephritis, IPG11406 is positioned to become a foundational disease-modifying therapy for a broad range of autoimmune conditions.
Mechanism of Action
EBI2 (also known as GPR183) is a G protein-coupled receptor that is overexpressed on a range of key pathological immune cells, including B cells, T cells, and macrophages. In multiple autoimmune diseases, EBI2 functions as a "cellular navigation system", directing these immune cells to migrate into target tissues, thereby initiating and amplifying inflammation and tissue damage.
As a potent, selective small-molecule antagonist, IPG11406 is specifically designed to block the EBI2-mediated signaling pathways, thereby preventing the migration of activated B cells, T cells, and macrophages into target tissues. In preclinical models, this reduces inflammatory cell infiltration and pro-inflammatory cytokine expression and attenuates disease progression by addressing the root cause of immune dysregulation.

Key Differentiation
■ Global First-in-Class Advantage: IPG11406 is the only EBI2 antagonist to have advanced to clinical trials worldwide, conferring a significant first-mover advantage in an underexplored therapeutic space.
■ Disease-Modifying Potential: By targeting the immune-cell trafficking central to autoimmune pathology rather than symptoms alone, IPG11406 has the potential to induce durable, treatment-free remission and reduce relapse rates.
■ Oral Administration Convenience: As a small-molecule drug, IPG11406 offers the potential to improve treatment convenience and accessibility compared with injectable biologics, while potentially reducing overall treatment costs.
■ Rapid Onset of Action: In the completed Phase 1b/2a trial in lupus nephritis, median 24-hour proteinuria declined from 1.97 g at baseline to 1.48 g by Day 58 (P=0.0248), with no rebound observed 30 days after treatment cessation.
■ Favorable Safety Profile: Preclinical and early clinical data indicate that IPG11406 is well tolerated, with no DLT or MTD identified in Phase 1 and wide safety margins demonstrated in GLP toxicology studies. No treatment-related Grade 3 or higher adverse events were observed in the Phase 2a trial.
Clinical Trials Summary
■ Phase 1 (Completed): A randomized, double-blind, placebo-controlled trial in healthy adult volunteers in China (N=66) was completed in March 2025, confirming safety, tolerability, and a favorable pharmacokinetic profile.
■ Phase 1b/2a (Completed): A multi-center, multiple-dose trial in patients with lupus nephritis was completed in China in August 2026. The results are highly encouraging: The complete renal response (CRR) rate was 22.7% overall, 50.0% among patients with biopsy-proven Class III/IV±V LN within 2 years of biopsy, and 75.0% among those within 6 months, showing a strong signal in patients with recent-onset active disease. Median 24-hour proteinuria declined from 1.97 g to 1.48 g at Day 58 (P=0.0248), with no rebound after treatment cessation.

IPG11406 Phase 1: Plasma concentration-time profiles by single-ascending-dose cohort
Current Status
Lupus Nephritis: The Phase 1b/2a trial was completed in China in August 2026. The Phase 2b trial, enrolling patients with biopsy-proven active LN, is expected to begin in the fourth quarter of 2026.
Ulcerative Colitis: A Phase 2 trial (144 patients; 12-week induction followed by 40-week maintenance) is underway in China with Peking Union Medical College Hospital as the leading site, and enrollment is ongoing.
Preclinical In vivo Efficacy
In preclinical studies, IPG11406 demonstrated dose-dependent therapeutic effects across multiple established animal models of autoimmune diseases:
• Systemic Lupus Erythematosus/Lupus Nephritis (SLE/LN): In the MRL/lpr mouse model, IPG11406 treatment resulted in significant, dose-dependent reductions in proteinuria, a key marker of kidney damage. It also markedly decreased inflammatory cell infiltration in the kidney, leading to a significant amelioration of glomerular and tubulointerstitial damage.
• Inflammatory Bowel Disease (IBD): In the Il10 knockout mouse model, IPG11406 produced a dose-dependent reduction in inflammatory cell infiltration in the colon and significant improvement in the overall colonic architecture, demonstrating its potential to control gut inflammation.
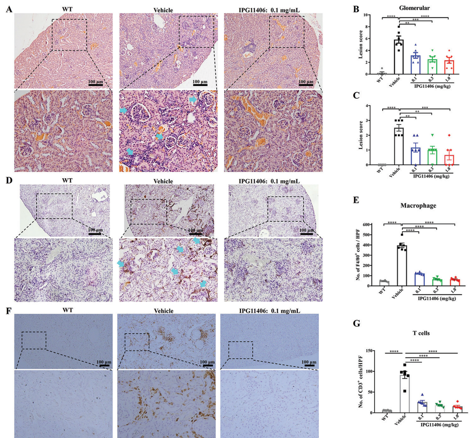
The changes in histological pathogenesis and inflammatory cell infiltration of the kidney in MRL/lpr mice.

Effects of IPG11406 on histopathological score of colon tissue in mice. (A) Inflammatory cell infiltration; (B) Histopathology score.
• Multiple Sclerosis (MS): In the experimental autoimmune encephalomyelitis (EAE) mouse model, IPG11406 treatment delayed disease onset and produced a dose-dependent decrease in clinical scores, indicating amelioration of MS-like pathologies.
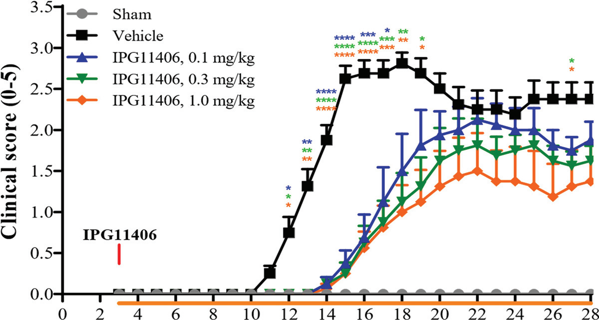
Clinical score of EAE mice treated with IPG11406. IPG11406 dose dependently reduced clinical score in the murine EAE model.
• Rheumatoid Arthritis (RA): In the CIA mouse model, IPG11406 dose-dependently reduced clinical arthritis scores and paw thickness, and attenuated body weight loss.

Publication
• Xi J, Gong H, Li Z, Li Y, Wu Y, Zhang Y, Wang JF, Fan GH. Discovery of a First-in-Class GPR183 Antagonist for the Potential Treatment of Rheumatoid Arthritis. J Med Chem. 2023 Dec 14;66(23):15926-15943. doi: 10.1021/acs.jmedchem.3c01364. Epub 2023 Dec 4. PMID: 38047891.
Cpyright © 2025 Nanjing Immunophage Biomedical Co.,Ltd
All Rights Reserved. 苏ICP备2022026466号-1  苏公网安备 32011202000830号







 Back

